
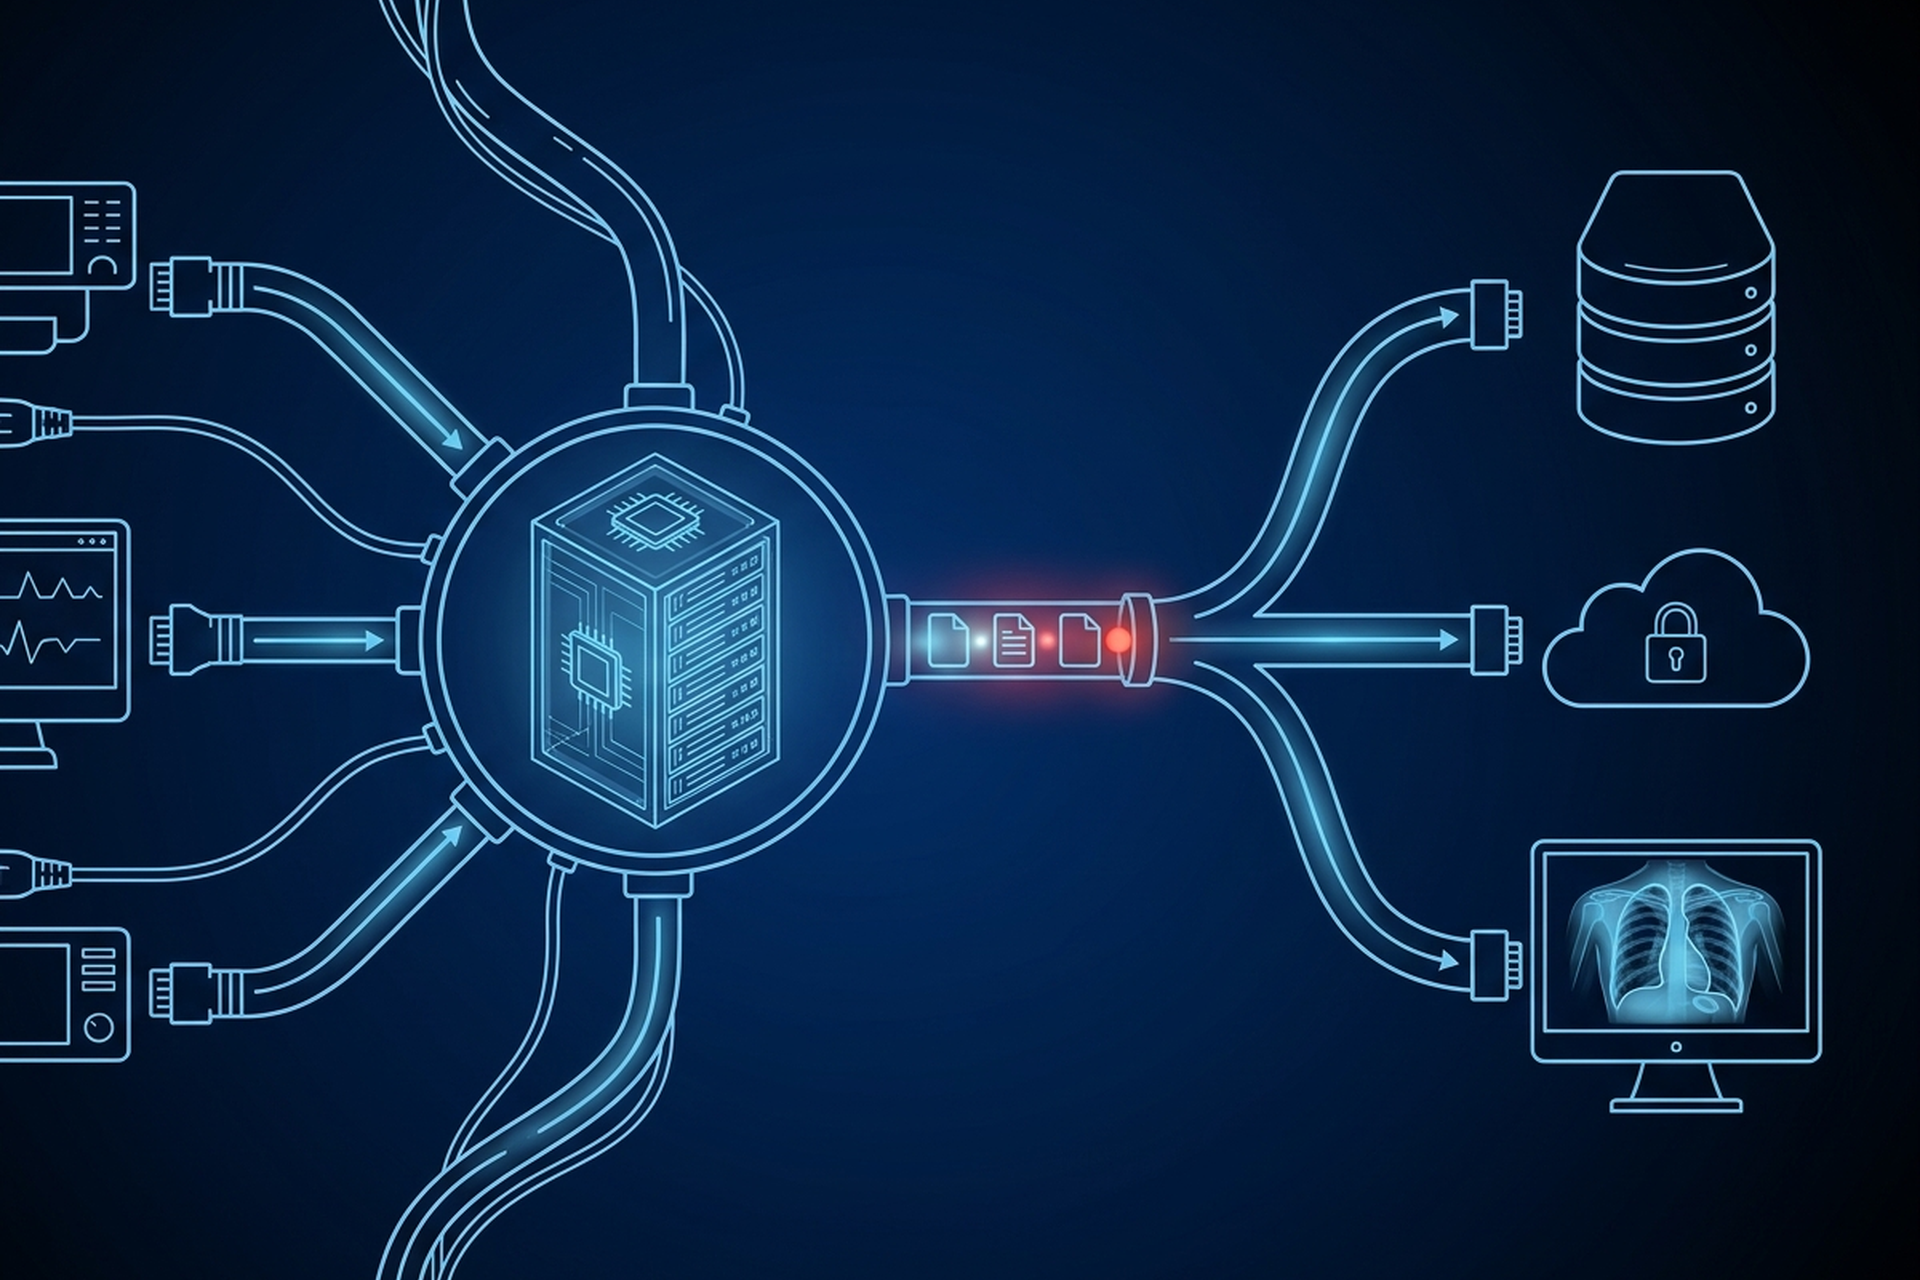
A department adds a second scanner, then a research archive, then a teleradiology partner reading nights and weekends, and each destination becomes one more connection a technologist configures by hand at the modality console. A DICOM router exists for the exact moment that stops working: one point every study passes through, where a rule engine decides where it goes next and normalizes what arrives. If a destination doesn’t answer, the router holds the study in its own queue and retries it. Direct modality-to-archive connections are simpler to picture, and they stop scaling the moment there is more than one place a study has to end up.
Why Direct Connections Stop Scaling
Three modalities feeding two archives is six connections to configure and keep working. Add a third archive and a teleradiology partner for night reads, and those three modalities are maintaining twelve connections total, each with its own AE Title pairing and failure mode if a destination goes offline.
A router collapses that mesh into a star. Every modality sends to one place, and N times M connections becomes N in and M out, with the router owning the rules for where a study goes. Each destination after that stops being a re-cabling project and becomes a rule added in one place.
Store-and-Forward Versus Pass-Through
A router operates in one of two basic modes, and the choice shapes most of what follows.
In store-and-forward mode, the router accepts an incoming study as its own receiving application, writes a local copy to its own queue, and only then initiates a separate transmission to each configured destination. Receiving and forwarding are decoupled: if a destination is unreachable, the study sits in the router’s queue rather than failing back to the modality. The modality’s own connection closes normally the moment the router has its copy, regardless of what happens downstream afterward.
In pass-through mode, sometimes called on-the-fly routing, the router forwards data as it streams in, without landing a complete local copy first. Latency is lower and storage overhead smaller, because nothing sits twice.
The tradeoff shows exactly when something goes wrong. If a downstream destination fails mid-transfer, there is often nothing durable to retry from, and the study has to be resent from the original source, if it still has it. Most production routers default to store-and-forward for that reason: a queue the router owns is what makes retry possible at all, instead of pushing every failure back onto the modality.
What a DICOM Router’s Rules Actually Match On
A routing rule is a condition against attributes a study already carries, paired with an action: forward, hold, or coerce first. The attributes that show up most in a real rule set are already sitting in the data by the time the router sees it.
| Attribute | What it identifies | A typical rule |
|---|---|---|
| AE Title | The Application Entity that sent, or is meant to receive, a study | Studies from one scanner’s AE Title go to the primary archive, a mobile unit’s to a separate destination |
| Modality | The type of device that acquired the study: CT, MR, US, and so on | Route ultrasound to one archive, cross-sectional modalities to another |
| Station Name | The specific machine within a department, not the modality type | Split two identical CT scanners into two different reading pools |
| Body Part Examined | The anatomy the study covers | Route chest studies to a chest-specific archive folder, separate from a musculoskeletal one |
| Time of day | A schedule layered on top of the router’s own logic, not a data attribute | Route after-hours studies to an on-call teleradiology destination as well as the primary archive |
The first four come directly out of the data set the DICOM object already carries. Station Name, for instance, is defined in the standard’s own equipment attributes as “User defined name identifying the machine that produced the Composite Instances,” exactly the granularity a rule needs to separate two identical scanners.
Body Part Examined works the same way, defined in the series attributes as “Text description of the part of the body examined.” None of these attributes were invented for routing. They exist in the data set for their own reasons, and a router reads them the way anything else does.
Rules also combine, and combining them is where fan-out happens: a study can match more than one rule at once and be forwarded to more than one destination. That means the primary archive always, plus a teleradiology destination only between 6pm and 7am, plus a research archive only if the body part and modality match what a department is actively collecting for.
Tag Morphing: Necessary and Dangerous
Sometimes a study arriving at the router doesn’t match what the destination expects, and forwarding it unchanged would break something rather than fix anything. DICOM’s Storage Service Class anticipates this directly. A receiving application may modify a narrow set of attributes, among them Patient ID and the Study and Series Instance UIDs, to coerce an incoming object into its own local model. It must also say so: a response carrying a coerced value comes back with a status of Warning, not Success.
The standard’s own example: an MR scanner assigns its own Study Instance UID, and an archive aware of the scheduling system may reassign it to match the study already expected. That is the necessary half. Two systems from different vendors, or two departments merging onto one archive, routinely disagree about identifiers for reasons that have nothing to do with either malfunctioning. A router is a reasonable place to reconcile that once, instead of asking every downstream system to tolerate every upstream vendor’s naming quirks.
The dangerous half is what the standard flags in the same breath: modifying an attribute another object uses to reference this one invalidates that reference, which is why doing so is strongly discouraged. A report signed against a study’s original UID stops resolving once a router downstream silently reassigns it. Two archives that each received a coerced copy of the same study, coerced differently, can end up disagreeing about how many distinct studies a patient has, and neither system’s logs will say so. What keeps tag morphing safe rather than merely convenient is that it stays visible: logged, attributable to a rule, applied the same way every time.
Retry and Queue Behavior When a Destination Is Down
Down, in DICOM terms, covers more than an obvious outage. A connection can be rejected outright, or accepted and then time out mid-transfer. A third case causes the most confusion later: a connection accepted and closed normally, while the receiving system never commits to keeping what it received.
That last case is what Storage Commitment exists to close. Plain storage transmission does not by itself require the receiving system to take responsibility for the data beyond accepting it: nothing obligates a destination to keep the study, only to acknowledge it arrived. Storage Commitment adds an explicit second step, where the sender asks the receiver to confirm, separately, that specific instances will be kept and retrievable later. A router that treats a successful transmission as proof of delivery, without checking that commitment, can mark a study delivered when the destination has done nothing more than acknowledge the bytes arrived.
In store-and-forward mode, an unreachable destination is a solvable problem: the study stays queued, and the router retries on a backoff schedule until the destination answers or an operator steps in. What makes that trustworthy rather than a black box is whether the queue is visible. A queue depth growing for six hours because a destination has been down since a maintenance window, unwatched, is functionally the same as data loss for anything time-sensitive.
Compression and Transfer Syntax Conversion in Transit
Every DICOM object declares exactly one transfer syntax, governing byte order, whether pixel data is compressed, and which scheme if so. A router forwarding a study to more than one destination is frequently forwarding to systems that don’t accept the same transfer syntax the modality sent. A bandwidth-constrained teleradiology link may need a study compressed that arrived uncompressed. A legacy viewer at a second site may only decode a syntax the primary archive’s modern workstation never has to think about.
A router handling either case has to actually transcode the pixel data, not just relabel it: decompress or recompress the bytes, then update the Transfer Syntax UID to match what it now contains. Skipping that second step produces a file whose header claims one encoding while its body holds another, something a conformant reader has no reason to distrust. That is why transfer syntax conversion is one of the more computationally expensive things a router does, and one of the easier to get subtly wrong at scale.
Prefetch: Moving Studies Before Anyone Asks
Routing is usually discussed as an outbound problem: a new study leaves the modality and has to reach the right place. Prefetch runs a version of the same rule engine in reverse, ahead of need. When a new exam is scheduled, prefetch logic queries the archive for a patient’s clinically relevant prior studies and moves them to the reading workstation before a radiologist asks. The comparison a reading depends on is already there, instead of triggering a manual retrieve mid-read.
Getting the matching right is genuinely hard, not a simple date lookup. A 2000 prefetch study measured two things separately. An algorithm mapping examination types into a small number of clinically relevant categories, rather than exact procedure codes, fetched the correct priors with a sensitivity of 98.3 percent and specificity of 100 percent. On-demand requesting of priors that had not been prefetched took 9.5 minutes on average.
Those 9.5 minutes are most of the case for prefetch as a routing function at all. Under-fetch, and radiologists fall back to the manual retrieve prefetch was meant to eliminate. Over-fetch, and the network absorbs load moving priors nobody needed.
Failure Modes: What Actually Goes Wrong
Three patterns show up more than any others once a router has run in production.
A silent drop happens when a study matches no forwarding rule, or a rule referencing a value that turns out malformed or missing, and the router logs an event nobody watches. Nothing crashes and nothing pages anyone. The gap surfaces only when someone reconciles what left the modality against what the archive received, a check that has to run on a schedule, not just after a complaint.
A duplicate send happens when more than one rule points at the same destination, or a retry fires after the original attempt already succeeded. If the destination doesn’t deduplicate on the study’s own identifiers, it lands twice, sometimes carrying attributes a coercion rule modified differently each pass, turning one duplicate into what looks like two distinct studies.
A backed-up queue happens when a destination stays down longer than planned and the router keeps accepting new studies with nobody watching. Every study is recoverable once the destination returns, but recoverable later is not the same as available now, for any reader who needed it already.
Frequently Asked Questions
What is a DICOM router in medical imaging?
A DICOM router is the single point every study passes through between modalities and their destinations. It matches each study against rules built on attributes the object already carries, then forwards, holds, or coerces it. Running it in store-and-forward mode gives the router its own queue, which is what makes retry possible.
What are the different DICOM modalities?
Modality (0008,0060) carries a defined term for the device, process or method that produced the series. CT, MR, US, CR, DX, NM, PT, XA and RF cover most imaging traffic. The list also includes non-image objects a routing rule easily misses: SR for reports, PR for presentation states, SEG and KO.
What is the communication standard used between PACS and imaging modalities?
DICOM, carried over TCP/IP. The modality pushes acquired images to the archive with C-STORE, and the archive answers C-FIND and C-MOVE for query and retrieve, with C-ECHO verifying the link. Scheduling arrives separately: the RIS, or a broker in front of it, exposes the DICOM Modality Worklist service the modality queries.
What This Means for a Product or Engineering Team
The questions worth asking a vendor follow from everything above. Is routing store-and-forward or pass-through, configurable per destination? Does the router check Storage Commitment before marking a study delivered, or trust a transmission alone? Is every coercion rule logged and auditable, not reconstructed from behavior?
Some deployments run routing as its own dedicated appliance, one more system with its own uptime to manage. Others build the same rule engine into the PACS platform itself. EBM mAIn PACS® runs DICOM server, storage, and routing together on EPS Pi, its edge appliance, where lifecycle and routing rules keep every study where it belongs.
Where Routing Sits in the Bigger Picture
None of what a router does is exotic once it’s named: match a study against its own attributes, decide where it goes, confirm it arrived, and hold it safely if it can’t. What makes the layer worth designing deliberately is that every one of those steps fails quietly by default.
This piece stayed deliberately on the routing layer itself. Every Imaging Product Has to Speak DICOM covers the service classes a router is built on. PACS Integration: Connecting Modalities, RIS, and the EHR covers the surface where a modality first associates with whatever is downstream, router or archive alike. Wherever a study ultimately lands, Vendor Neutral Archive: Buying Storage That Outlives Your PACS covers what to test once it gets there.
A router that surfaces what it did is doing the same job as one that hides it. Only one of them is debuggable when a destination has been down since lunch and nobody noticed.